
Gastric bypass revisions
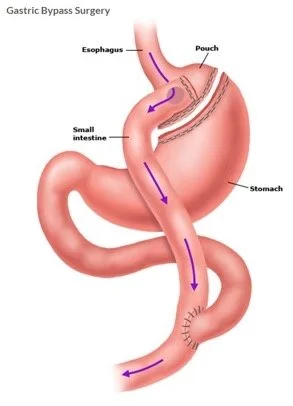
The gastric bypass is used to achieve weight loss in patients with severe obesity. Some patients lose less than expected despite the surgery; others develop complications later. In either case, revision surgery can restore the weight loss or correct the problem.
These symptoms usually get worse rather than better on their own. If any of what follows sounds like your experience, it's worth being seen sooner rather than later.
Symptoms worth acting on
Most people adapt to these gradually and stop noticing them. If you're doing any of the following, it's worth getting looked at.
Heartburn or reflux getting progressively worse, with medication no longer controlling it.
Difficulty swallowing that makes you choke or vomit when you eat, lie down or try to sleep.
Epigastric pain — in the area between the chest and the abdomen.
A diet that has quietly narrowed — living mostly on liquids, sauces and light crunchy foods because you can't manage anything solid, dry, dense or doughy.
Weight loss significantly below what was predicted, or weight that has come back.
Weight loss significantly above what was predicted. Losing faster than expected is also worth investigating, not just celebrating.
What might be happening
Those symptoms point to one of a handful of complications. Which one it is determines what can be done about it.
-
Marginal ulcer
An ulcer at the join between the pouch and the small intestine. A common cause of epigastric pain after bypass.
-
Stricture
The pouch outlet has narrowed — sometimes to the point of high-grade obstruction, where very little can pass through.
-
Gastro-gastric fistula
The pouch has reconnected itself to the old remaining stomach, so food bypasses the intended route. A frequent cause of weight regain.
-
Heartburn, reflux or hiatal hernia
Several different problems can present this way, and they're treated differently.
-
Incarcerated or herniated pouch
The pouch has become trapped or herniated up into the chest. More common in patients who were converted from a sleeve to a bypass.
-
Biliary reflux, gastritis or esophagitis
Bile irritating the stomach and esophagus. It can feel identical to ordinary acid reflux, which is why it often goes untreated for a long time.
-
A large or horizontal gastric pouch
The pouch holds more than intended, or sits in an orientation that limits how well the operation works.
How we diagnose it
Two studies, done by a bariatric surgeon who performs revision work, will usually show what has changed since your original operation.
Upper GI swallowing study
A live X-ray of you swallowing, showing how the pouch and its outlet are functioning and whether anything is narrowed, displaced or reconnected.
Upper endoscopy
A camera passed into the stomach to look directly at the pouch, the outlet and the esophagus — and to find ulcers and inflammation an X-ray cannot show.
The conversation
After both studies it's usually clear what's causing the problem. Your surgeon will then go through what can and cannot be corrected, and what each option would mean for you.
Your options
Which of these applies depends entirely on what the studies show. Not every problem needs another operation — several are managed medically or endoscopically.
- Changing your medication regimen
- Starting a new medication
- Stretching the gastro-jejunostomy, where there's a stricture
- Revision of the gastro-jejunostomy — the pouch outlet
- Reducing the pouch size or the anastomosis size
- Hiatal hernia reduction, with repair of a pouch trapped in the chest
- Reversing the bypass operation
Let's find out what happened
Make an appointment to talk through your symptoms and arrange the studies. Only once we know what's changed can we tell you how to fix it.
Had a different operation? See all revision options.