
Roux-en-Y gastric bypass
The gold standard against which other weight loss operations are measured — the oldest, the best studied, and the second most common in the United States after the sleeve.
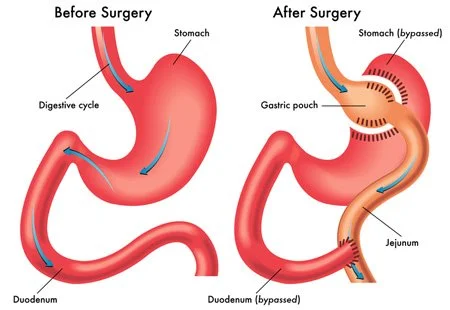
The bypass works two ways at once. A small stomach pouch with a narrow outlet restricts how much you can eat; rearranging the small intestine reduces how much of what you do eat gets absorbed. On top of both, it produces metabolic changes with real health benefits — most dramatically on diabetes, which often improves before any significant weight has come off.
Small incisions — the whole operation is laparoscopic
Of excess weight typically lost, half of it in the first six months
Of patients maintain their weight loss long term, with good compliance
Typical meal size once settled, three to four times a day
How it works
Building the pouch
Five small incisions. The first step is creating a new stomach — the pouch — from the very top of your existing stomach, using modern stapling devices. It can be made as small as your thumb, and it's completely separated from the old stomach. A large part of the old stomach may be removed to induce stronger metabolic effects and reduce hunger further.
The old stomach stays a living organ; it simply never sees food again. Because it's still there, the bypass can be reversed if that ever becomes necessary.
Rearranging the intestine
The second step reroutes the small intestine so that less of it is involved in absorbing food — without removing any of it. The point where digestive enzymes meet your food is moved further downstream, roughly 100 cm past the pouch. The intestine is divided once and reconnected in two places, and the resulting shape is a Y — which is where the name comes from.
The length of each segment can be adjusted to produce more or less malabsorption. More bypassed bowel means more weight loss, and also more risk and more side effects. Your surgeon will discuss where that balance should sit for you.
Why it changes hunger
The pouch limits how much you can eat; the narrow outlet controls how quickly it empties. The longer the pouch stays full, the longer satiety lasts. For many patients the most striking part isn't the restriction — it's being released from constant hunger.
The bypass is a tool
Surgery alone will not produce lasting weight loss. The operation will force many patients to change how they eat, but we don't want anyone relying on that alone. How much weight comes off depends on how well you use the tool and follow the rules — which is why the rules class and support group matters as much as the operation does.
Am I a candidate?
Candidacy for any weight loss surgery is based on Body Mass Index — a calculation using height and weight together, since 300 pounds means something very different at five feet than at six.
Criteria most insurers use
Qualifies regardless of other medical problems.
Usually with an accompanying condition: type 2 diabetes, hypertension, sleep apnea or other respiratory disorders, non-alcoholic fatty liver disease, osteoarthritis, lipid abnormalities, gastrointestinal disorders or heart disease.
Where type 2 diabetes is not well controlled. Most insurers do not yet cover surgery on this basis, though the clinical case is established.
In addition
- No endocrine cause of obesity, such as untreated hypothyroidism
- An acceptable operative risk — the procedure should not put you at undue risk
- You understand the surgery and its risks
- No drug or alcohol addiction
- No uncontrolled psychological conditions
- You have made other attempts at weight loss — diet, exercise, medication, counselling
Insurers often add their own criteria. Our office can tell you what yours requires — call 913-322-7408.
What to expect
The medical and emotional benefits begin almost immediately; the cosmetic ones follow in their wake. Conditions related to obesity often start resolving before the weight loss is complete, and your need for medication usually falls as they do.
- Significant, sustained weight loss
- Blood sugar normalised or dramatically improved, often within the first year
- Lower or normal blood pressure
- Lower or normal cholesterol
- Lower doses of medication, or none
- Relief from sleep apnea, severe acid reflux and urinary stress incontinence
- Less arthritis pain in the lower back, knees and hips
- Improved mobility and exercise endurance
- More energy
- Improved mood and self-esteem
- Progression of heart disease halted or slowed
- Improvement in many lung conditions
How much weight
Most patients lose around 70% of their excess weight, with the greatest loss over the first year to eighteen months and half of it in the first six. Reported figures run to roughly 60% of excess weight by six months and 77% by twelve; at five years, patients maintain around 50% on average.
With good compliance, about 80% of patients maintain their weight loss long term, and 80–90% see improvement or resolution of their other medical problems. Some regain is normal — typically 10–15% after five years.
Risks
Every operation carries risk. The decision to proceed rests on the treatment being less harmful than the disease being treated — a judgement you make with your surgeon, not one anyone should make for you.
In skilled hands, the risk of dying within thirty days of a gastric bypass is around 0.5%. Serious complications — a clot in the lung, a leak at a connection, bleeding, wound infection — occur in around 5% of cases. Done laparoscopically rather than open, the hospital stay is shorter, wound problems are fewer and recovery is more comfortable.
Specific complications
- Perforation or injury of the stomach or intestine
- Leakage from a connection or staple line, causing infection
- Spleen injury requiring removal, or injury to other organs
- Narrowing or stretching of the pouch outlet
- Small bowel obstruction
- Blood clots in the legs
- Pulmonary embolism — a clot in the lung
- Inability to eat certain foods
- Gallstones or gallbladder disease
- Inflammation of the pouch, pouch ulcer or marginal ulcer
- Internal hernia
- Failure to lose satisfactory weight, or weight regain
- Instrumentation failure, which may require further surgery
Dumping syndrome
Stomach contents emptying too quickly into the small intestine, usually triggered by sugar or a large sweet meal. Nausea, weakness, sweating, faintness and sometimes diarrhoea after eating. It isn't generally dangerous, and it's unpleasant enough that most patients simply stop eating sweets — which is arguably a benefit disguised as a side effect.
Nutrition, for life
Bypassing the duodenum reduces absorption of iron and calcium, which predisposes to iron deficiency anemia — a particular concern if you already lose blood through heavy periods or bleeding hemorrhoids. Chronic anemia from vitamin B12 deficiency can also occur, managed with tablets or injections.
Women, already at risk of osteoporosis after menopause, should know that bypassing the duodenum has caused metabolic bone disease in some patients — bone pain, loss of height, curvature of the spine, and fractures of the ribs and hips.
All of these are preventable. Lifelong supplementation — vitamin B12, iron, folate and calcium — plus proper diet and attending your follow-ups will manage every one of them. This is not optional, and it does not stop after the first year.
Two things to know
Pregnancy is not recommended during the first eighteen months, while active weight loss is happening.
The bypassed portion of the stomach and duodenum cannot easily be seen with X-ray or endoscopy afterwards, which matters if a problem ever develops there.
Advantages and disadvantages
Advantages
- Reliable, long-lasting weight loss
- Highly effective for putting obesity-related conditions into remission, diabetes above all
- A refined, standardised technique with decades of evidence behind it
- Can be reversed if it ever becomes necessary
Disadvantages
- Technically more complex than a sleeve gastrectomy or gastric band
- More vitamin and mineral deficiencies than the sleeve
- Risk of small bowel complications and obstruction
- Risk of ulcers, particularly with NSAID or tobacco use
- May cause dumping syndrome after sweet food or drink
- Requires lifelong supplementation, dietary discipline and follow-up
This is your decision to make
Choosing between operations is genuinely complicated, and educating yourself is the important first step. Everything here is background — you'll learn substantially more in an hour with one of our bariatric surgeons than from any website.
Comparing options? See the sleeve gastrectomy. Travelling a long way? Tell our staff when you book and we'll keep the number of trips down.