
Sleeve gastrectomy
The most commonly performed weight loss operation in the United States, also called the vertical sleeve gastrectomy. It works mainly by restriction — controlling how much you can eat at one time — with metabolic effects that improve health and weight loss further.
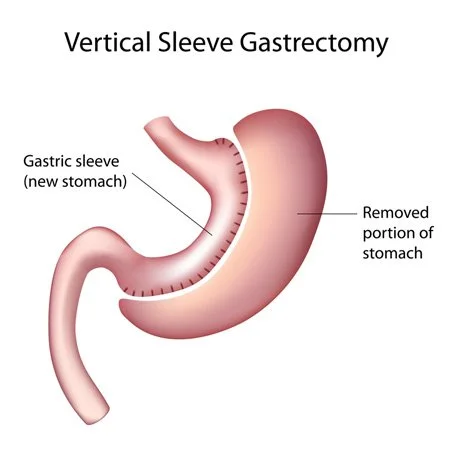
More than 85% of the stomach is removed, specifically the portion that stretches most to accommodate food. What remains is stapled vertically into a narrow tube. Digestion and absorption are unchanged; the difference is capacity, and what that does to hunger.
Of the stomach removed — the most stretchable portion
Of excess weight typically lost, comparable to gastric bypass
Over which that loss occurs — half of it in the first six months
Typical meal size from about six months onward, three to four times a day
How it works
Reducing the stomach
The laparoscopic sleeve gastrectomy is a restrictive operation: it reduces the size of the stomach and with it your capacity to eat a large amount at one sitting. The part removed is the part that stretches most. The normal digestive process is not altered — food absorption and digestion continue as before.
The new stomach is created with stapling devices that cut and seal at the same time. A bougie — a long, smooth-tipped, flexible sizing tube — is placed into the stomach first, and the surgeon staples along it. That produces a consistent result every time, with a lumen roughly the diameter of a coin.
Why it changes hunger, not just capacity
The length and narrowness of the new stomach limit how much you can comfortably eat, and the longer the pouch stays full, the longer satiety lasts. The operation also causes favourable changes in gut hormones that suppress hunger and reduce appetite — which is why patients typically lose more than restriction alone would explain. For many people, being released from constant hunger is the most striking part of the experience.
The restriction is similar to what a bypass patient experiences: ultimately about four ounces of food, three to four times a day, with prolonged fullness from that small amount.
The sleeve is a tool
Surgery without permanent changes to eating habits and lifestyle will not produce lasting success. The operation and its metabolic effects push many patients toward those changes, but we don't want anyone relying on that alone. The sleeve significantly helps with the work — it doesn't replace it. Education and compliance are what keep the weight off.
Am I a candidate?
Candidacy for any weight loss surgery is based on Body Mass Index — a calculation using your height and weight together, since 300 pounds means something very different at five feet than at six.
Criteria most insurers use
Qualifies regardless of other medical problems.
Usually with an accompanying condition: type 2 diabetes, hypertension, sleep apnea or other respiratory disorders, non-alcoholic fatty liver disease, osteoarthritis, lipid abnormalities, gastrointestinal disorders or heart disease.
Where type 2 diabetes is not well controlled. Most insurers do not yet cover surgery on this basis, though the clinical case is established.
In addition
- No endocrine cause of obesity, such as untreated hypothyroidism
- An acceptable operative risk — the procedure should not put you at undue risk
- You understand the surgery and its risks
- No drug or alcohol addiction
- No uncontrolled psychological conditions
- You have made other attempts at weight loss — diet, exercise, medication, counselling
Insurance companies often add their own criteria. Our office can tell you what yours requires — call 913-322-7408.
What to expect
The medical and emotional benefits begin almost immediately after surgery; the cosmetic ones follow in their wake. Conditions related to obesity often start resolving before the weight loss is complete.
- Significant, sustained weight loss
- Portion control
- Blood sugar normalised or dramatically improved
- Lower or normal blood pressure
- Lower or normal cholesterol
- Relief from sleep apnea, acid reflux and urinary stress incontinence
- Less joint pain in the lower back, knees and hips
- Improved mobility, stamina and exercise endurance
- More energy
- Improved mood and self-esteem
- Progression of heart disease halted or slowed
- Improvement in many lung conditions
- Reduced need for medication
How much weight
Patients lose around 70% of their excess weight over one to one and a half years, with half of that in the first six months. Reported figures run to roughly 60% of excess weight by six months and 77% by twelve; at five years, patients maintain around 50% of their excess weight loss on average.
A worked example
A patient weighs 300 lbs, and their ideal weight is 100 lbs — so they carry 200 lbs of excess weight.
At 70%, the expected loss is about 140 lbs. Around 70 lbs of that would typically come off in the first six months.
Your own numbers will differ. This is arithmetic, not a prediction — your surgeon will give you a realistic figure based on your starting point and your health.
Risks
Every operation carries risk. The decision to proceed rests on the treatment being less harmful than the disease being treated — which is a judgement you make with your surgeon, not one anyone should make for you.
The sleeve carries more risk than a Lap-Band and less than a bypass. Most of that risk comes from cutting the stomach: a very long staple line on a new, long, narrow stomach. Any staple line can leak, bleed or become infected.
Specific complications
- Leakage from a staple line, causing infection
- Spleen injury, potentially requiring removal
- Esophageal injury
- Narrowing or stricture of the sleeve
- Blood clots in the legs
- Pulmonary embolism — a clot in the lung
- Inability to eat, or difficulty eating, certain foods
- Gallstones or gallbladder disease
- Inflammation of the sleeve lining, or sleeve ulcer
- Failure to lose satisfactory weight, or weight regain
- Instrumentation failure, which may require further surgery
- Anemia, vitamin or mineral deficiency, protein malnutrition, temporary hair loss
Pregnancy is not recommended during the first year and a half, while active weight loss is happening. Other complications not listed here can also occur.
Women are already at risk of osteoporosis, particularly after menopause, and should be aware of heightened potential for bone calcium loss. Chronic anemia from vitamin B12 deficiency can occur, and is usually managed with supplements. All of the deficiencies above can be prevented and managed with proper diet and vitamin supplementation — but they need attention for life, not just for the first year.
Advantages and disadvantages
Advantages
- Technically simpler, with a shorter operating time
- Can be performed in some patients with high-risk medical conditions
- May be a first step for patients with severe obesity
- Can serve as a bridge to a gastric bypass or SADI-S procedure later
- Effective weight loss, with improvement in obesity-related conditions
- Causes favourable gut hormone changes that suppress hunger and improve satiety
Disadvantages
- Not reversible — the removed stomach is gone
- May worsen existing reflux, or cause new reflux and heartburn
- Less metabolic impact than bypass procedures
This is your decision to make
Choosing between operations is genuinely complicated, and educating yourself is the important first step. Everything on this page is background — you'll learn substantially more in an hour with one of our bariatric surgeons than you can from any website.
Travelling a long way to see us? Tell our staff when you book — we'll plan your visits to keep the number of trips down.